

Obsessive-Compulsive Disorder (OCD) is a complex and highly individualized condition. While the core cycle of obsessions and compulsions is universal, the themes and content of these experiences can differ dramatically from person to person. Understanding the wide variety of OCD subtypes is crucial for accurate diagnosis, effective treatment, and self-compassion. This guide synthesizes clinical knowledge, research-backed strategies, and clarifies important distinctions, including the difference between OCD and related conditions like Body-Focused Repetitive Behaviors (BFRBs).

Why Recognizing Subtypes Matters
Reduces shame: Realizing your symptoms are shared by others helps counter isolation.
Improves treatment: Tailored approaches address the unique challenges of each subtype.
Fights stigma: Highlighting OCD’s diversity dispels stereotypes about “just being neat.”
The Mechanism Behind Every Subtype
Regardless of whether an obsession centers on germs, intrusive violent thoughts, or relationship doubts, every OCD subtype is driven by the exact same cycle:
Trigger: A situation, image, memory, or bodily sensation occurs.
Obsession: An unwanted intrusive thought or "what if" enters the mind.
Distress: The brain misinterprets the thought as an active threat or moral failure.
Compulsion: A physical or mental action performed to relieve anxiety or seek certainty.
Temporary Relief: The anxiety drops briefly, which reinforces to the brain that the compulsion was necessary.
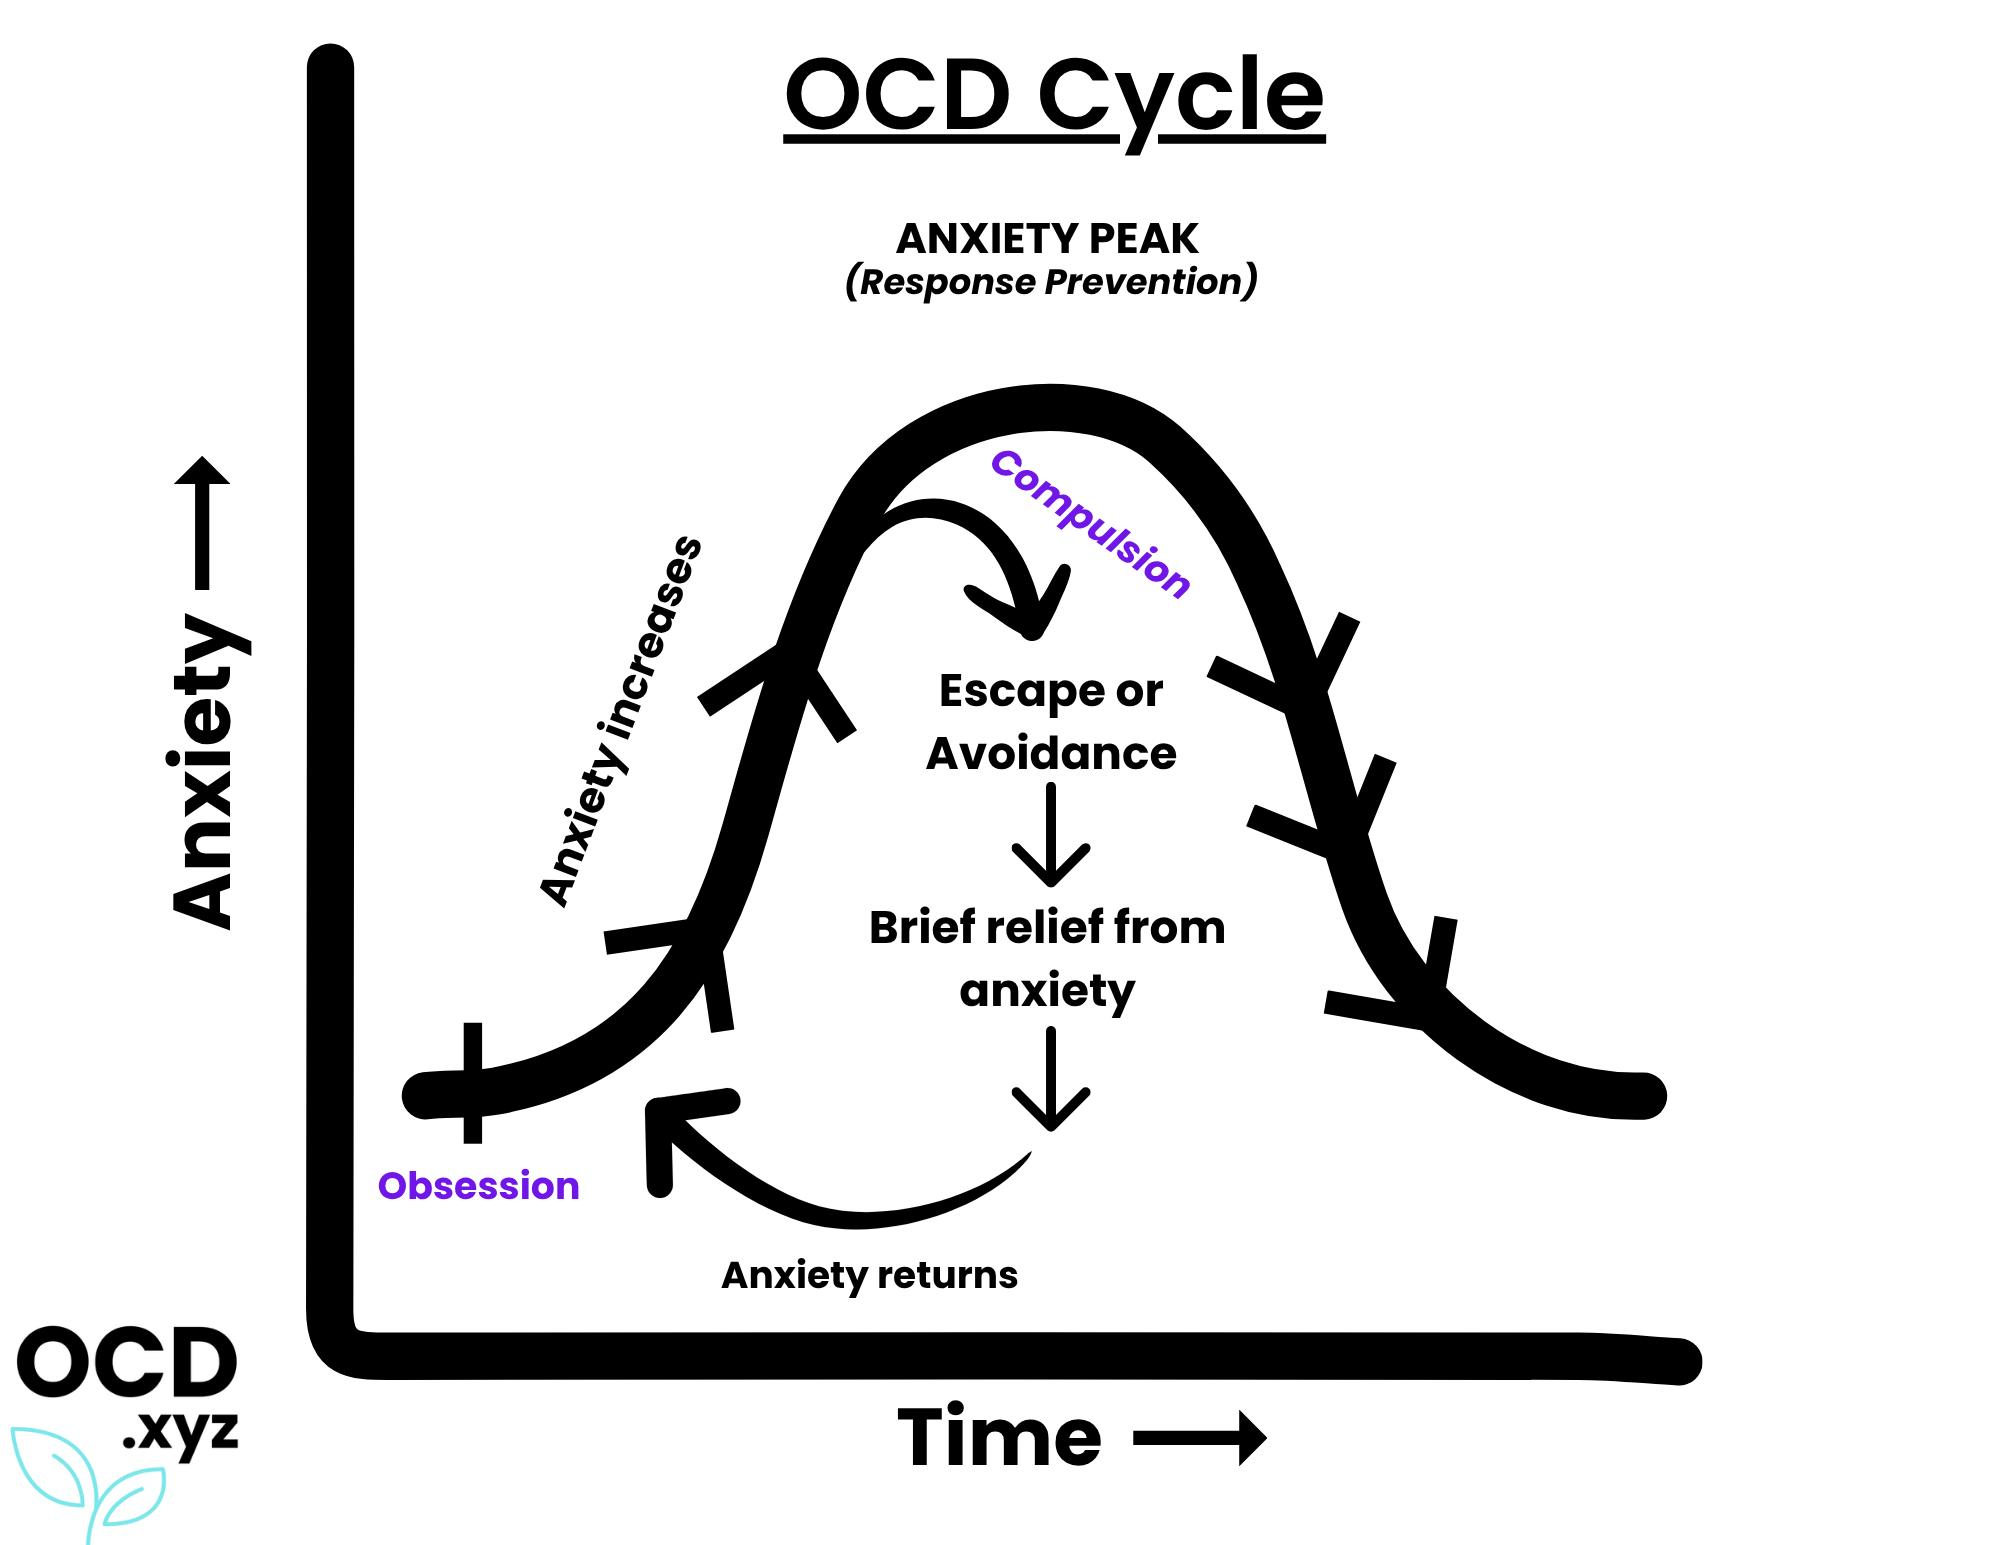
The OCD Subtype Spectrum
Below are the most recognized OCD subtypes. Many people experience more than one at once, and themes can shift over time. All are treatable with evidence-based strategies like Exposure and Response Prevention (ERP).
Contamination OCD
Obsessions: Fear of germs, chemicals, or even “emotional” contamination.
Compulsions: Excessive washing, cleaning, avoidance of public spaces, ritualized decontamination.
Example: A nurse fears touching doorknobs will infect patients, leading to 2-hour handwashing sessions.
Treatment Insight: ERP might involve touching a “contaminated” object and delaying handwashing.
Harm OCD (Including Suicidal OCD)
Harm OCD involves intrusive, distressing thoughts or images about causing harm—either to others or oneself. These obsessions are ego-dystonic: unwanted, contrary to the sufferer’s values, and cause significant anxiety and shame. Compulsions include avoiding potential triggers (like knives or high places), seeking reassurance, or mentally reviewing one’s actions.
Suicidal OCD is a specific manifestation of Harm OCD, where obsessions center on intrusive fears of dying by suicide or losing control and harming oneself. These are not true suicidal desires, but rather terrifying “what if” thoughts (e.g., “What if I lose control and hurt myself?”). The person’s fear is of acting against their will, not a wish to die. Compulsions may include avoidance, reassurance-seeking, or checking for signs of intent.
Key distinction: In Suicidal OCD, the thoughts are unwanted and distressing, while in true suicidal ideation, thoughts are ego-syntonic and may involve intent or planning.
Checking OCD
Obsessions: Fear of causing harm or making a mistake by being careless (e.g., leaving the stove on, doors unlocked).
Compulsions: Repeatedly checking locks, appliances, or seeking reassurance from others.
Example: A person checks the stove and door locks dozens of times before leaving home.
Relationship OCD (ROCD)
Obsessions: Doubts about a partner’s suitability or one’s own feelings (“Do I really love them?”).
Compulsions: Analyzing interactions, comparing relationships, seeking reassurance, avoiding intimacy.
Example: A person repeatedly asks friends, “Does my partner seem right for me?”
Treatment Insight: ERP could involve writing a feared thought (“I don’t love them”) and resisting the urge to seek reassurance.
Sexual Orientation OCD (SO-OCD)
Obsessions: Doubts about one’s sexual orientation, regardless of prior certainty.
Compulsions: Mental checking of attractions, avoiding LGBTQ+ spaces, researching online.
Example: A heterosexual man fears he’s gay and avoids male friends.
Treatment Insight: Exposure to triggers (e.g., watching an LGBTQ+ themed movie) without analyzing feelings.
Pedophilia OCD (POCD)
Obsessions: Unwanted, terrifying sexual thoughts, images, or bodily sensations regarding children, which run entirely counter to your values and cause intense horror, disgust, and shame.
Compulsions: Avoiding children or family gatherings, checking groin sensations (groinal responses) for arousal, compulsively reviewing past interactions with kids, or seeking constant self-reassurance.
Example: A teacher or loving parent fears being near children out of terror that an intrusive thought means they are secretly a monster or a threat.
Key Distinction: In POCD, intrusive thoughts are ego-dystonic—they are unwanted, horrifying, and cause extreme distress because they violate the person's moral character. True pedophilia involves ego-syntonic sexual attraction and desire, with an absence of distress regarding the attraction itself.
Treatment Insight: ERP involves reading news articles, being in public spaces near families, or writing stories about feared scenarios without engaging in groin checking, mental reviewing, or asking for reassurance.
Scrupulosity (Religious/Moral OCD)
Scrupulosity involves an obsessive fear of violating moral, ethical, or religious standards. It goes far beyond healthy spirituality or conscientious values, trapping the individual in hypervigilant anxiety over being "immoral," "sinful," or "a bad person."
Scrupulosity typically manifests in two main forms:
Religious Scrupulosity
Obsessions: Fears of sinning, displeasing God, blasphemy, losing one's salvation, or performing religious rituals incorrectly.
Compulsions: Excessive praying, repeating prayers until they feel "pure," compulsively confessing minor thoughts to clergy or partners, and seeking reassurance about salvation.
Example: Reciting a specific prayer 50 times because a "bad thought" crossed your mind mid-prayer, fearing God will punish your family if you don't start over.
Moral (Non-Religious) Scrupulosity
Obsessions: Hyperfixation on absolute moral perfection, honesty, justice, and ethics. Terrifying doubts about being secretively selfish, malicious, racist, or a bad person.
Compulsions: Over-analyzing everyday decisions for potential moral harm, compulsively confessing minor omissions or white lies, mentally reviewing past interactions to verify your motives were 100% pure, or avoiding situations where a moral choice might arise.
Example: Spending hours analyzing whether buying a specific brand of coffee makes you complicit in human rights violations, or confessing to a co-worker that you secretly thought their presentation was boring because you feel dishonest keeping it to yourself.
Important Note on Belief Systems & Fluidity
Themes are not restricted by personal beliefs. Deeply religious individuals frequently experience non-religious moral obsessions (e.g., hyperfixating on tax form honesty or business ethics), while secular, agnostic, or atheist individuals can experience religious-themed intrusive thoughts (e.g., sudden fears of going to hell, intrusive blasphemous imagery, or fear of cosmic retribution). OCD simply hijacks whatever the brain registers as a catastrophic loss of moral or spiritual integrity.
Key Distinction: Healthy Values vs. Moral Scrupulosity
The crucial line of division comes down to flexibility vs. rigid panic:
Healthy Morality & Faith: Guided by values, empathy, and personal principles. It brings a sense of meaning, connection, and growth, allowing for human imperfection, nuance, and forgiveness.
Moral/Religious Scrupulosity: Driven by fear, guilt, and intolerance of uncertainty. It demands 100% moral certainty and absolute purity in every thought, word, and action, leading to exhausting rumination, self-punishment, and hyper-checking of one's motives.
Differential Diagnosis: Ruling Out Schizophrenia & Psychosis
Because religious and moral themes can also present in schizophrenia and spectrum disorders, careful clinical assessment of reality testing is vital:
In OCD (Ego-Dystonic & Intact Insight): Intrusive thoughts are recognized as coming from within the person's own mind. The individual retains insight, recognizing the thoughts as unwanted, distressing, and irrational—even if the anxiety feels overwhelming.
In Psychosis / Schizophrenia (Ego-Syntonic Delusions): Religious or moral beliefs present as delusions or auditory/visual hallucinations (e.g., believing God or an outside force is physically inserting thoughts into their head, or that they are directly receiving divine commands). Insight is typically absent or severely impaired, and the belief is held as objective reality.
Treatment Insight: ERP and I-CBT involve practicing sitting with moral or spiritual ambiguity (e.g., making a decision without knowing if it is 100% ethically perfect) and resisting the urge to confess, ruminate, or seek moral reassurance from others.
Symmetry/“Just Right” OCD
(Including Perfectionism and Related Behaviors)
Symmetry or “just right” OCD is characterized by an overwhelming need for things to feel balanced, orderly, or symmetrical. Obsessions may focus on discomfort or anxiety if objects, actions, or even bodily sensations don’t feel “right.” Compulsions include arranging, repeating, evening out movements, or checking actions until the sensation of “rightness” is achieved.
Body-Focused Repetitive Behaviors (BFRBs):
Sometimes, individuals with symmetry or “just right” OCD may engage in behaviors like mirror checking or even hair pulling—not due to appearance concerns, but to relieve discomfort associated with things not feeling symmetrical or “just right.” For example, someone might pull at hair on one side of the head to match the other, or repeatedly check their reflection to ensure balance.
Important distinction:
These behaviors should be carefully differentiated from Body-Focused Repetitive Behaviors (BFRBs) such as trichotillomania (hair-pulling) and excoriation disorder (skin-picking), which are classified separately from OCD.
BFRBs are typically not preceded by intrusive thoughts or obsessions, but are performed to regulate emotions or out of habit, and may be experienced as pleasurable or relieving.
OCD-related behaviors are driven by obsessions and performed to alleviate anxiety or discomfort about things not being “just right.”
Incompleteness / "Not Just Right" Sensations: Unlike Harm or Contamination OCD—which are driven by fear of a specific catastrophe—this theme is driven by an intolerable physical or mental sensation that an action, sentence, or movement wasn't performed "correctly" or completely. Compulsions involve repeating actions (like stepping through a doorway or re-reading a line) until an internal "click" or sense of balance is achieved.
Assessment tip:
If repetitive behaviors like hair pulling or mirror checking are present, clinicians should assess whether these are responses to intrusive, obsessional discomfort (suggesting OCD) or are more habitual, emotion-regulating behaviors without obsessions (suggesting a BFRB).
Magical Thinking OCD
Obsessions: Belief that certain thoughts, numbers, or actions can influence unrelated outcomes (“If I think about a plane crash, it will happen”).
Compulsions: Performing rituals, avoiding “bad” thoughts, repeating actions to “neutralize” danger.
Example: A teen taps their desk 10 times to stop a parent from dying.
Counting OCD
Obsessions: Need to count objects, steps, or actions to prevent harm or achieve a sense of completeness.
Compulsions: Counting aloud or in the mind, repeating actions a certain number of times.
Example: Counting steps to the car to prevent a loved one’s illness.
Existential OCD
Obsessions: Overwhelming doubts about reality, purpose, or existence (“What if nothing is real?”).
Compulsions: Researching philosophy, seeking reassurance, mental rumination.
Health Anxiety OCD
Obsessions: Fear of having a serious illness.
Compulsions: Body checking, Googling symptoms, frequent doctor visits.
Sensorimotor/Somatic OCD
Obsessions: Hyperawareness of automatic bodily functions (breathing, blinking, swallowing).
Compulsions: Monitoring sensations, trying to control them, seeking reassurance.
Real Event OCD
Obsessions: Guilt or doubt about past actions (often minor or misinterpreted).
Compulsions: Mental review, confessing, seeking reassurance
False Memory OCD
Obsessions: Terrifying doubts about whether you committed a harmful, immoral, or embarrassing act in the past (e.g., "What if I hit someone with my car yesterday and didn't notice?").
Compulsions: Mentally replaying past events, checking local news, retracing your driving route, or asking others for reassurance.
Key Distinction: The brain misinterprets vague or absent memories and fills in the gaps with worst-case scenario dread.
"Pure Obsessional" OCD ("Pure O")
Obsessions: Any intrusive theme where compulsions are non-visible or mental.
Compulsions: Mentally replaying conversations, self-reassurance, excessive researching, or hypervigilance.
The "Pure O" Myth: A common misconception is that "Pure O" involves obsessions without compulsions. In reality, compulsions are always present—they are just covert. For example, a person might spend hours mentally reviewing a conversation to ensure they didn’t say something offensive.
Responsibility OCD
Obsessions: Excessive worry about being responsible for harm or wrongdoing.
Compulsions: Checking, confessing, seeking reassurance, mental review.
Postpartum and Perinatal OCD
Obsessions: Fears of harming the baby or being a “bad parent.”
Compulsions: Avoiding the infant, excessive sterilizing, seeking reassurance.
Treatment Across Subtypes
Exposure and Response Prevention (ERP) is effective for every OCD subtype. The key is tailoring exposures to the specific obsession and resisting associated compulsions. For example:
Contamination OCD: Touch a doorknob and delay handwashing.
ROCD: Write a feared thought (“My partner is wrong for me”) without seeking reassurance.
Harm OCD: Hold a knife while cooking and sit with the anxiety.
Medication (SSRIs, clomipramine) can reduce symptoms, especially when combined with therapy. A rule out for Bipolar Disorder is important because SSRIs can trigger mania and hypomania.

When to Seek Help
If OCD interferes with daily life, relationships, or joy, consult a specialist. Use the International OCD Foundation’s directory to find providers trained in ERP.
Key Takeaways
OCD has dozens of subtypes—each valid and treatable.
Themes often overlap or shift over time.
ERP therapy is the gold standard, regardless of subtype.
Recovery is possible with the right support.
This guide is for informational purposes and does not replace professional care. For diagnosis and treatment, consult a licensed provider.
